Pregnancy in Dubai

Advice & information on common pregnancy problems by a Fetal & Maternal Medicine Consultant


Leave a comment

Pain relief in labour Epidural


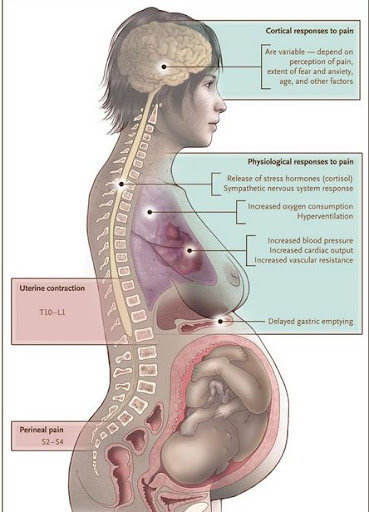
How mothers perceive their birthing experience a large extent depends on how they deal with labor pain. Giving birth is painful. It is well accepted that pain during labouris severeand usually exceeds the mother’s expectations. 
It has been describedby some, as the worst pain a woman experiences. Although many mothers are able to deal with it well for some is overwhelming. 
Sometimes the maternal reaction -over reaction to the pain can adversely affect the labor/fetus.
The most effective to deal with pain during labourare the various regional techniques for pain relief.
What is epidural anesthesia?
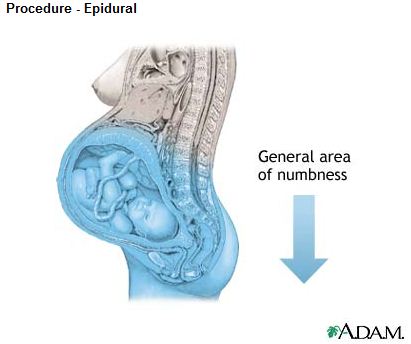


Epidural is a popular techniqueof regionalanesthesia. It is called regionalas it blocks sensation– painat a certainpart regionof the body.


How does it work?
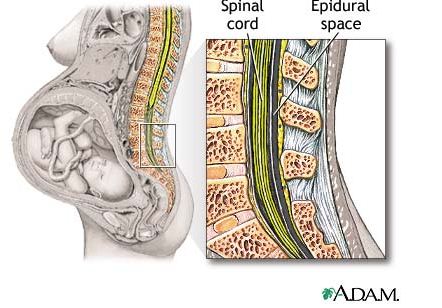
It works by stopping the pain signal transmission at the lower nerves of the spine.As a resultit numbs the lower part of the body. This is achievedby a “cocktail” of local anesthetic medication and special opioids.


Read more about how epidural is set up what are the advantages and disadvantages using it as pain relief for your labor


How is itsetup?
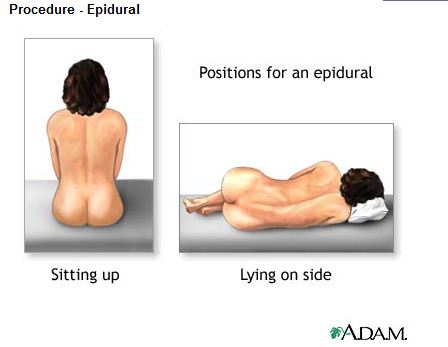

The nurse or the midwife will first placea cannula to have access to your veins and ensurethat you receiveintravenous (through the vein) fluids. This is maintainedthroughout the labour. Then the anesthetist will cometo setthe epidural. They will usually either ask youto situp or lie on your side. In both casesthey will require youto try and archyour back  “like an angrycat” you may hear them say. This helps them a lot to find the right spacefor placing the epidural catheter. 
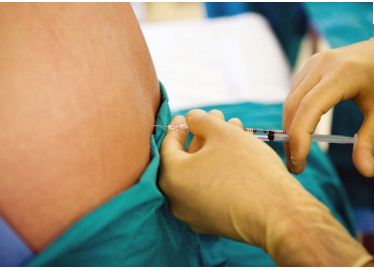

The anaesthetist will use an antiseptic solution to cleanyour back in order to minimise the risk for infection. Using a fine needle he will injectlocal anesthetic and numb the areahe is planning to placethe epidural catheter.
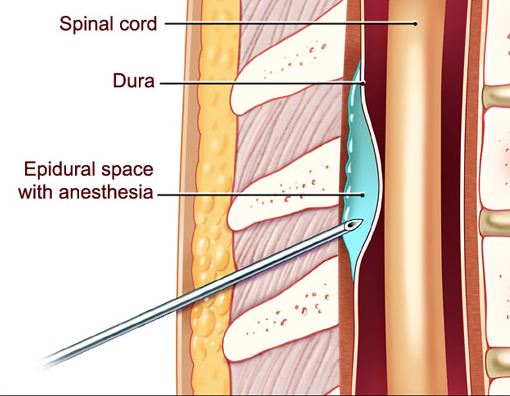


He will then inserta needle via the numbed area to the epidural space. Youusually feela pushing sensation at that point. Using the needleas a guidehe threads a verythin plastictube to the epidural space.
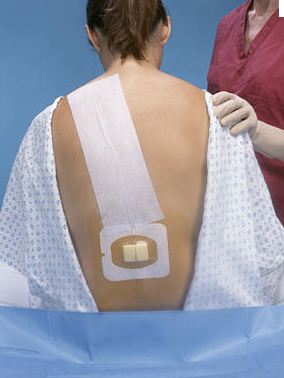


Then the needle is removedand the catheter is securedwith plastic tape.This catheter is usedto deliverthe medication during the labour. This initially is doneby a directbolus injection followed by a continuous infusion


What are there different types of epidural used in labor? What is a walking epidural?


There are essentially two variations of the epidural technique used. 


1. Routine Epidural ; as described earlier


2. Combined Spinal Epidural (CSE) or “walking epidural”. The difference with this technique is that by using a special verythin needle the initial dose of medication is givento the intrathecal space (a layer further in from the epidural space).The advantage of this technique is that it has its effectmuch faster and alsopreserves your motor control (ieyou can controlyou muscle better) allowing to move more freely at your bed. Although it is calledwalking epidural it is not commonly recommended to walkas your balancewith beaffected. 

Each Hospital unit uses customised protocols regarding the medications and instruments used.


2.What are the side effects – complications of the epidural in labour?


1. Youmay feel shivering, nausea, or itching on some occasions you may experience backache or soreness where the needle was inserted.

2. It may cause a sudden drop of your blood pressure (BP). The midwife should keep a close eye on the BP and ensure youare receiving adequate fluids. In some casesthe anesthetist may have to give you specificmedications to deal with verylow BP


3. On occasions youmay havebreakthrough painor not completecoverage of the pain. Usually the anesthetist will try to remedythis by extra doses of medication or on occasions replacing the epidural catheter.

4. Severe headache. This complicates about 1% of procedures and it is dueto leakage of spinal fluid from the site of the needle placement.It can be devilishly severe headache and usually is aggravatedby movements. Most of the time the treatmentis conservativewith painkillers and hydration but some times aprocedurecalled “bloodpatchmay be offered to improve symptoms.
Normally the anesthetist will come and fully explain what happened andfollowyouup.

5. Very rarely, severe infectionor nerve damage can be caused by the insertion of the needle

How will an epidural affect my labor?

Positive effects



• It is the best modeof pain relief available for labor pain. It allows youto get some restduring labor.


• It can be used to cover medical procedures like instrumental deliveries, repair of tears or episiotomy even a Cesarean sectionif needed.

• It is easier to controlthe deliveryof the fetal head as the extreme pain elementis not there.


• It allows you to be alert with a clear mindthroughout labor. This helps mothers to “enjoy” the labourwithout the pain. Many find crucialto be ableand maintain a clear mindand decision making abilitywithout being distractedby the relentless contraction pain.


Negative effects

• More medical interventions; youwill need access to your veins, continuousmonitoring of your baby. It is more common that you will need syntocinon – oxytocin to ensure good strong contractions and it is recommended that you have a urinary catheter to help you emptyyour bladder. These are common tasks and in some units many will be done anyway even if you do not have an epidural.

• You are confinedto your bed.

• It is more common to need help with the use of a ventouseor forcepsto deliver the baby especially if youhave a “heavyepidural” meaning verylittle muscle control. 

Myths


Do Epidurals increase the risk for CS? NO.There is now goodevidence that the CS rate is not increased using an epidural.

Do epidurals increase the length of labor? Yes by 15 min.So a well-managed epidural is not expected to have any significant effect to the length of labour.

Do epidurals affect my baby? A well working epidural does not affect your baby’s well being. However side-effect like sudden drop of your blood pressure can cause fetal distress if not dealt timely and appropriately.


When is the earliest stage inlabourthat I can have an epidural?



The commonadvice is to opt for an epidural at the active phase of the first stage of labor i.e.| 3-4 cm dilatation of the cervix with regular contractions.

In realityif youneed pain relief and either you membranes have ruptured or they are accessibleand can be rupturedyou can have an epidural.


Are there situations that Iwill be refusedan epidural if Iaskfor one?

1. You are in advanced in labourand the team feels that youwill deliverbefore they have time to provideyou and effective epidural.

2. The anaesthetist is busyor there isn’tenough staff to look youafter safely. On occasions in very busylabor wardsthere might not be enough trained staff to safely look youafter with an epidural.

3. Youtake medication that affect how your blood clots like heparin or warfarin or your pregnancy is complicatedby conditions that affect your bloods clotting ability. In these situationsthere is riskfor having a bruise– hematoma at the place of the needle insertion. Given that the spinal canal is a confined space, hematoma can affect adversely your nerves and spinal cord.

4. Youhave or suspected to have an infectionthat has spread to your blood stream

What shouldyoudo in advance ;

Mother-

It is importantto discuss your pain relief options when youare building your birth plan with your midwife / obstetrician. This will allow time,  at a non stressful environmentto explore the optionsavailable for you. It will make it possible to bring to light your fears and answeryour questions.

  • The D day                                                                                                                                                                                              
Inform the staff that is looking after you regarding your preferences for pain relief. 

Be flexible, realistic and ready to adapt. Now, this can be very challenging given that there is a good chance that you will be anxious, tired and in a lot of discomfort. 

Labour wards can on occasions be very busy places. You have the disadvantage that you are not usually aware of what else is going on at the floor. So  make your midwife your best friend – ally. Let her know what you want for pain relief and listen to her advice. Ask her to help you in choosing the better time for the epidural. Although you are the one in pain the midwife will know what is happening at the rest of the labour ward rooms, how busy the anaesthetist is and whether there are any cases that may have an impact on staff availability when you need your epidural. 

Obstetrician Risk assessment

Your obstetrician should be able to identify factors that can may makeregional anesthesia more riskyand difficult.Typical examples are ; previous spinal injury or spinal operations, scoliosis, high BMI. Particular fears like fear of needles or a bad previousexperience can make the procedure verydifficult.
Be forthcoming with your Doctor and let him/her know if you have particular worries about pain relief in labour.  

In these cases early review preferably  by a senior anaesthetist will help appropriate planning for the delivery day. 

Dr George Michailidis, Obstetrician and Gynecologist 

Fetal and Maternal Medicine Consultant 

Leave a comment

Pain relief in labour; psychoprophylaxis, relaxation, pethidine, epidural. What is the best option? Part 1 labour pain, psycho prophylaxis

Pain relief in labour; psychoprophylaxis, relaxation, pethidine,  epidural.  What is the best option?

Part 1 labour pain, psycho prophylaxis

One of the common discussion points during the preparation of the birth plan are the pain relief options during labour.
Understanding the labour pains;
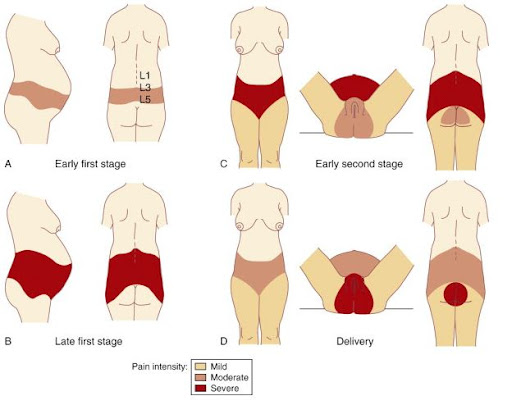
Labour is a painful process. During active labour the contractions come about every 3 min and last a good 40 sec. During the first stage of labour (when the neck of the womb is opening up) women have generalised abdominal (tummy) pain mainly originating from the contracting uterus (womb) and the dilating cervix (neck of the womb). During the second stage of labour (when the mother tries to push the baby out) more sharp pain comes from the distension – stretching of the vagina and the perineum by the baby’s head.  All women do experience pain during normal labour and most would describe this pain becoming very intense at some point during labour.
The threshold for pain is different for different people. Even for the same person how much pain she can tolerate changes depending on her physical and emotional state. In general our pain threshold becomes lower as we get more tired and more anxious.
Pain is a complex phenomenon. It has both a sensory (what our nerve fibres transmit) and an emotional part (how our brain interprets the signal) and a great ability to get our attention and dominates over other cognitive (thinking and emotional) processes.
There are two main approaches in dealing with labour pains
1.Non pharmacological / psycho-prophylactic  approach
2.Pharmacological (use of drugs)
Psycho prophylaxis;
It includes a number of methods that help the mother deal with labour pains. Examples are gentle massage, relaxation techniques, breathing exercises. One of the most well known is the Lamaze approach to childbirth ( www.lamaze.org ).

At their web site you can find a wealth of information for pregnancy and childbirth.

 These methods do not change the intensity of the pain but they do alter the perception of pain and they reduce maternal suffering.  Although pain and suffering usually occur together it is possible in the same way that you can have suffering without pain to have pain without suffering. Psycho prophylaxis helps women interpret the pain as a normal part of labour so they do not feel threaten from it and find it easier to cope with it.
Different methods have different approaches but one of the great advantages of all is that they include extensive education regarding the normal labour process. By providing quality education they prepare the mother to deal with it better and reduce the anxiety of the unknown.
One major disadvantage is that some of the teaching settings is the following; while dealing with pain without medication is praised, use of drugs is considered as failure. Achieving a balanced approach is the best way forward. Rather than adopting a hard line approach for everyone, having personalised plan for each client works best.  By putting the mother as the centre piece of the birth plan it is possible to cater for the individual needs and wishes.  This avoids the huge emotional stress and negative feelings of failure that some women are left with when they decide to use medications for pain relief.

Fetal & Maternal Medicine Specialist
Obstetrician & Gynecologist


1 Comment

Vaginal birth after a Cesarean Section

More than one in five deliveries in Dubai are done by Cesarean Section. A lot of women – couples are trying to find the right answer to the question; “What is the best way to deliver my baby if I had one previous Cesarean Section ?”


Recently the American College of Obstetricians updated its guidelines regarding vaginal deliveries after cesarean section (VBAC). The new guidelines are less restrictive. The main changes are in respect of where mothers should give birth and what are the group of mothers who should be considered for a VBAC or TOLAC (trial of labour after a cesarean section). This change has already started attracting media attention.
Most of the obstetric organisations in the world (ACOG – USA, RCOG – UK, SOGC – Canada, RANZOG – Australia) have a similar approach stating that “delivery is recommended at an establishment that can offer immediate delivery  if needed ” .
In the US, most likely due to the high risk of medicolegal action, it led  a large number of smaller hospitals to refuse care to women who had a previous ceasarean section ( CS ) and wanted to try for a vaginal delivery. The new approach by the ACOG supports the mothers autonomy of decision as to where and how she should deliver her baby. At the same time it gives a lot of emphasis in the counselling process and information provision. This is extremely important as you can only make an informed choice when you have the right information.
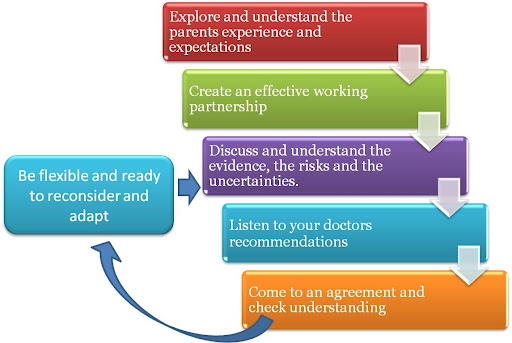
 In Dubai most of the large private hospitals are able to offer care to women who wish to try for a VBAC. All women should have the opportunity to discuss with their obstetrician how they would like to deliver. So take your time and discuss it with your doctor and formulate your birth plan.  This is my suggestion as to how you should approach your consultation / decision making;
1.   Your doctor should try and explore your previous experiences and understand your expectations. A lot of the decision making is coloured from what happened last time. Some mothers feel traumatised from a prolonged and unsuccessful labour and do not want to go through the same again. Others feel that they missed out on their opportunity for a vaginal birth and really want to try their best to achieve a vaginal delivery.

2.   One of the advantages of private care is the opportunity and the time  to build a working partnership between the parents and the doctor. So take full advantage of it and utilize it to help you make up your mind.
3.    Discuss the evidence and try to understand its strengths and its weaknesses. It is important to understand the uncertainties particularly when you try and tailor the available evidence to a certain case.
4.   Listen to your doctor’s recommendations. In addition to the widely accepted evidence they should reflect the local realities. It is good to read the evidence on the internet but implementing them at a local level is different and your doctor will be the best person to advise you on this.
5.    Come to an agreement  This includes checking that everybody fully understands what is decided.
6.   Always be flexible ready to reconsider and adapt. Pregnancy and in particular labour are dynamic developing scenarios. The main objective though remains the same ” a healthy mother and a healthy baby”. Parents need to be ready to reconsider and adapt as the situation changes.  Typical examples are; ” what do you do if while you decided for an elective CS you present to labour ward in advanced labour ? ” , ” what do you do if while you decided to go for a VBAC you labour you have 40 weeks and nothing happened ?”
In my experience the parents approach varies from one couple to another.  Some parents come with a clear plan while others may need time to come to formulate in their mind what they feel is best for them.
You might find helpful the following basic statistics.
·The overall chance of a successful VBAC is between 70-80%. This is an overall figure . Your doctor should be able to adjust this figure and give you an assessment tailored to you. There are a number of factors that increase or decrease your chance for a successful vaginal birth after cesaerean section.  Your past obstetric history (what happened in your last pregnancy), your medical history, the progress of the current pregnancy, how your labour starts are all factors that make a difference.
·Risks; whatever you decide to do you need to have a good idea of the risks for you and your baby.
Labor is a risky time of a woman’s and her baby’s life. Whichever mode of delivery you choose there are some risks. 
Elective cesarean section to deliver your baby after one previous Cesarean section;
·It is more likely that you will stay in hospital longer and will need a longer time for recovery. You have to recover from a major surgical procedure.
·There is increased risk for surgical complications like injury of the bladder and the bowel. The more cesarean sections you have the more likely to run in these troubles. After every operation during the healing process you create adhesion (organs and tissues sticking together). This makes future operation in the same site (like a repeat CS ) more risky.
·There is increased risk to have problems in future pregnancies. These mainly have to do with the location of placenta and the risk for it to become very adherent to the womb (placenta accreta).
·Your delivery is more likely to be by CS next time as well.
Vaginal birth after one previous Cesarean section – successful
·There is a risk for uterine rupture. The chance for this happening is small (0.5%) it can lead to serious problems for both mother and baby.
·There is a risk for complications during the labour. Sometimes these can be serious. The risk for perinatal death or hypoxic encephalopathy (brain damage) is almost 0.5/1000.
·With every vaginal delivery there is a risk of vaginal tear and significant perineal (this is the area between the vagina and the back passage) trauma.
Unsuccessful trail of labour after one previous Cesarean section
The worst of both worlds suffer those who try for a vaginal birth but fail and end up with and emergency CS.
·Every operation performed in and emergency setting is more risky that an elective -scheduled one. As a result of that all the risks mentioned for the elective CS are increased in this scenario.
·Furthermore it is more likely to have a large bleed that requires transfusion, or ends up to a hysterectomy.
·More likely to have an infection.
·More likely to have to stay in hospital for longer and take longer time to recover.
I hope you find this info useful
Dr George Michailidis
FURTHER READING

ACOG patient education leaflet; Vaginal birth after Cesarean Section

Dr George Michailidis, Obstetrician and Gynecologist 
Fetal and Maternal Medicine Consultant